
FUPA vs Diastasis Recti: Understanding the Difference
Page Contents
- What is the difference between FUPA and diastasis recti?
- FUPA describes an external contour
- Diastasis recti involves the abdominal wall
- The linea alba: why the gap sits in the midline
- FUPA vs diastasis recti at a glance
- Fat, muscle gap or both? A side-by-side guide
- Why is the distinction useful after pregnancy?
- How is abdominal separation assessed?
- Look beyond a finger-width measurement
- Prepare useful details for your appointment
- How to do a gentle self-check at home
- Could posture be making it look worse?
- What can help, and when should you seek care?
- Match support to the concern
- Do not dismiss a new lump as FUPA
- How to get pelvic health physiotherapy in the UK
- Frequently asked questions
- Can I have a FUPA and diastasis recti at the same time?
- Will a belly binder close the separation?
- Can men have diastasis recti?
- Does diastasis recti make a FUPA look bigger?
- Can diastasis recti close on its own?
- Is surgery ever needed for diastasis recti?
FUPA vs diastasis recti is a comparison between fullness around the pubic area and a change in the abdominal wall. They can occur together, especially after pregnancy, so a lower-belly bulge does not tell you which tissues are involved. A photograph or home check cannot replace an assessment.
What is the difference between FUPA and diastasis recti?
FUPA describes an external contour
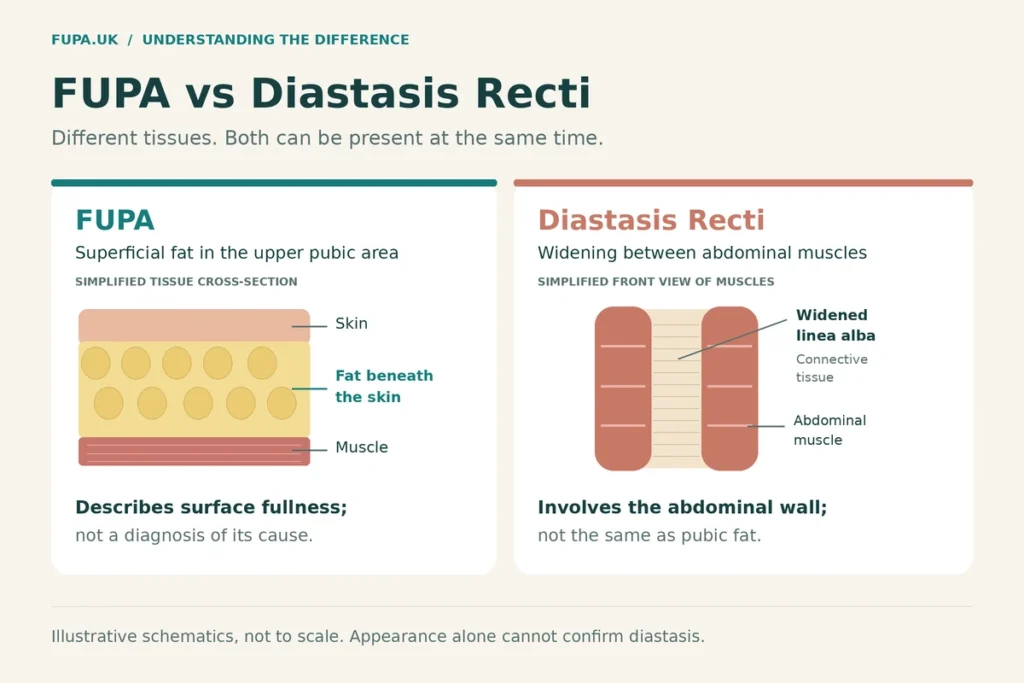
FUPA is an informal term for fat around the upper pubic area. People sometimes use it more loosely for a lower-belly fold, which may include skin as well as subcutaneous fat. It is not a medical diagnosis. Our guide to where the FUPA is located explains the distinction.
Diastasis recti involves the abdominal wall
The rectus abdominis muscles run down the front of the abdomen. Between them is connective tissue called the linea alba. Diastasis recti describes widening between these muscles as that central tissue stretches and thins. It does not mean that pubic fat has moved into a muscle gap. Cleveland Clinic explains the anatomy.
That difference matters when choosing support. A concern about clothing fit is a different starting point from difficulty managing everyday movement.
The linea alba: why the gap sits in the midline
The linea alba is a band of tough connective tissue that runs from the breastbone (the xiphoid process) down to the pubic bone. It forms where the sheets of the three flat abdominal muscles, the external oblique, internal oblique and transversus abdominis, meet in the middle.
The two strips of the rectus abdominis sit either side of it. In diastasis recti, the linea alba stretches and thins, so the distance between the two strips, known as the inter-rectus distance, increases. The muscles have not torn; the tissue joining them has lengthened.
This is why diastasis shows up along the centre line, and most often around or above the navel. A FUPA sits lower and further out, in the fat over the mons pubis. The two can overlap visually, but they involve different layers: one is in the fat beneath the skin, the other is in the abdominal wall itself.
FUPA vs diastasis recti at a glance
| Question | FUPA | Diastasis recti |
|---|---|---|
| What does it describe? | Fullness involving superficial fat, sometimes with loose skin | Widening between the paired abdominal muscles |
| Where is it? | Upper pubic area; sometimes used loosely for the lower belly | Abdominal midline, around, above or below the navel |
| Can appearance confirm it? | The word describes appearance, not its complete cause | No; clinical assessment is needed |
| Can both be present? | Yes. An external fold does not rule out an abdominal-wall change. | |
If your main concern is fullness that fluctuates during the day, the separate FUPA vs bloating comparison addresses that question. Avoid using one label for every abdominal change.
Fat, muscle gap or both? A side-by-side guide
Because the two can look alike from the front, it helps to compare how each one behaves. The table below describes typical patterns, not rules, and a clinician should confirm anything that worries you.
| What you notice | Mostly FUPA (fat or skin) | Mostly diastasis recti | Both together |
|---|---|---|---|
| Where it sits | Over the pubic bone, below the waistband | Along the midline, often around the navel | Lower pouch plus a soft midline |
| Pinch test | A thick fold you can grip | Little to pinch; the softness is deeper | A fold, with a soft channel above it |
| During a small head lift | No change in shape | A ridge or doming along the midline | Doming above a pouch that stays put |
| Lying flat | Pouch spreads but remains | Belly often looks flatter at rest | Midline softens; pouch remains |
| Who usually helps | GP, dietitian or surgeon, depending on goals | Pelvic health physiotherapist | Physiotherapist first, then other options |
Why is the distinction useful after pregnancy?
Pregnancy commonly separates the abdominal muscles as the uterus grows. Skin, fat and abdominal-wall recovery are separate considerations, so the phrase “postpartum belly” does not identify one cause.
The NHS post-pregnancy guide advises contacting a GP if a muscle gap remains obvious eight weeks after birth. This is a point for seeking assessment, not a deadline your body must meet. Ask sooner if symptoms are troubling you.
For the wider recovery context, read our FUPA after pregnancy guide. Here, the useful question is narrower: are you concerned about the surface contour, abdominal support, or both?

How is abdominal separation assessed?
Look beyond a finger-width measurement
You may notice abdominal doming when sitting up or a softer area around the navel. These observations are worth mentioning, but cannot establish the cause. A clinician can examine the abdomen; ultrasound may help when more precise measurement is needed.
The European Hernia Society guidelines use a separation wider than 2 cm to define rectus diastasis. That measurement is not, by itself, a prescription for treatment. Assessment should consider symptoms and how the abdominal wall functions.

Prepare useful details for your appointment
Write down when you first noticed the change, which activities bring it out, whether it hurts and what you want help doing. Mention previous abdominal surgery and any pregnancy or birth history. This gives the appointment a clearer purpose than trying to match your stomach to an online photograph.
How to do a gentle self-check at home
A home check will not diagnose anything, but it can help you describe what you have noticed. Stop if it causes pain, and wait until you have been cleared after birth or surgery before trying it.
- Lie on your back with your knees bent and feet flat on the floor.
- Place your fingertips across the midline of your belly, just above your navel, with your fingers pointing towards your feet.
- Relax, then lift your head and shoulders slightly off the floor, as if starting a very small curl.
- Feel for a soft channel between two firmer edges, and note roughly how many fingers fit and how deep they sink.
- Repeat at the navel and a few centimetres below it.
Pay attention to depth and firmness as well as width. A gap that feels soft and deep, or a ridge that domes upwards during the lift, is worth mentioning to a clinician. So is anything that feels different from one day to the next.
Next, gently pinch the tissue just above your pubic bone. If you can grip a thick fold there, that fullness is fat or skin rather than the muscle gap. Many people find both, which is exactly why the two labels are best kept separate.
Could posture be making it look worse?
Posture changes how both problems look. When the pelvis tips forward, known as anterior pelvic tilt, the lower belly is pushed outwards and the lower back arches. A small FUPA then appears larger, and a weak midline has more pressure pressing against it.
Habits such as holding your stomach in all day or breathing mainly into your chest can add to that pressure. Our guide to FUPA and posture includes a simple wall test for pelvic tilt and the stretches that usually help.
A physiotherapist will often look at posture and breathing alongside the abdominal gap, because improving how pressure is managed through the trunk is a large part of most rehabilitation plans.
What can help, and when should you seek care?
Match support to the concern
For suspected diastasis, ask about pelvic health physiotherapy. The European Hernia Society says physiotherapy may be considered before surgery, but the evidence does not establish one exercise programme as best for everyone. A plan should be chosen for your needs rather than copied from a “flat belly” challenge.
NHS advice recommends avoiding sit-ups, planks and high-impact exercise initially after birth, alongside avoiding heavy lifting and straining. Discuss when and how to progress. Stop an exercise that causes pain and seek advice. General FUPA exercise information is not an individual rehabilitation prescription.

Do not dismiss a new lump as FUPA
A hernia is different from diastasis, although they can coexist. A hernia involves tissue pushing through a gap or weak area. See a GP if you think you have one. The NHS hernia guidance advises urgent help from NHS 111 if a hernia is accompanied by pain, vomiting, constipation or a bloated abdomen.
You can also ask for help with persistent discomfort, leaking urine or difficulty with daily tasks. There is no need to prove that a visible gap is “large enough” before describing a problem.
How to get pelvic health physiotherapy in the UK
Start with your GP, midwife or health visitor. Mention the gap, any doming, back pain or bladder symptoms, and ask about a referral to women’s health or pelvic health physiotherapy. The postnatal check at around six to eight weeks is a natural time to raise it, but you can ask at any point.
In some areas you can refer yourself to NHS physiotherapy without seeing a GP first. Check your local NHS trust or the NHS physiotherapy page for what is available near you.
If you choose to go privately, the Pelvic, Obstetric and Gynaecological Physiotherapy network (POGP) is the professional group for physiotherapists who specialise in this area. Look for someone registered with the Health and Care Professions Council (HCPC), which every practising physiotherapist in the UK must be.
Surgery is usually discussed only after a period of rehabilitation, and mainly when symptoms continue. Repair is often combined with a tummy tuck when loose skin or a FUPA is also a concern, but cosmetic procedures are rarely funded by the NHS.
Frequently asked questions
Can I have a FUPA and diastasis recti at the same time?
Yes. Superficial fullness and abdominal muscle separation involve different tissues. One does not rule out the other.
Will a belly binder close the separation?
A binder may offer temporary support, but it does not heal the separation or strengthen the core. Discuss its use with your clinician.
Can men have diastasis recti?
Yes. It is not limited to pregnancy. A persistent midline bulge or concern about abdominal support warrants assessment.
Does diastasis recti make a FUPA look bigger?
It can. A weaker midline gives the lower belly less support, so an existing FUPA may push further forward. Improving abdominal support can change the shape, although it will not remove the fat itself.
Can diastasis recti close on its own?
The gap often narrows in the months after birth. Whether it closes fully varies, and function matters more than width. Pelvic health physiotherapy can help if symptoms continue.
Is surgery ever needed for diastasis recti?
Sometimes, usually when symptoms persist after rehabilitation or a hernia is also present. Surgery is not required for appearance alone, and a surgeon will discuss risks and recovery first.
General health information. Sources were checked on 29 September 2026. Illustrations are conceptual and are not diagnostic images.